

Infection prevention and control is the area where care homes face the most scrutiny and the smallest margin for error. Close living, shared facilities, and residents who are frailer than the general population mean an outbreak spreads fast and hits hard. The practical challenge is not knowing what good IPC looks like, it is evidencing that it happens consistently, on every shift, between inspections.
So, how can care homes navigate these challenges effectively? Let’s explore the key principles for infection prevention and control in care homes, and actionable steps care homes can take to reduce infection risks.
- What Are the Most Common Sources of Infection in Care Homes?
- What are Infection Prevention and Control (IPC) Principles?
- What Does CQC Require for Infection Control in Care Homes?
- How Do You Improve Infection Control in a Care Home?
- Enhance Infection Control in Care Homes with GoAudits
- Care Home Infection Control Audit Templates
- FAQs
What Are the Most Common Sources of Infection in Care Homes?
Infection spreads through a chain of six links: pathogen, reservoir, portal of exit, means of transmission, portal of entry, and susceptible host. Breaking any link stops transmission, and breaking more than one gives greater protection. In care homes, the links most often broken in practice are transmission (hand hygiene, PPE, cleaning) and portal of entry (catheter and wound care).
The 6 links are:
- Pathogen
- Reservoir
- Portal of exit
- Means of transmission
- Portal of entry
- Susceptible host

Let’s address the common sources of infection in care homes that form part of the above chain of infection link.
Human Interaction
Close and regular contact between staff, residents, and visitors facilitates the transmission of infections. This includes the spread of respiratory viruses (such as influenza and COVID-19), gastrointestinal infections (like norovirus), and other common infections like MRSA.
Environmental Contamination
Surfaces, equipment, and shared facilities can become contaminated with pathogens. These include door handles, medical equipment, communal areas (like dining rooms and lounges), and residents’ personal items. Improperly cleaned and disinfected environments provide a reservoir for pathogens to survive and spread.
Inadequate Hand Hygiene
Failure to perform hand hygiene at key moments, such as before and after contact with a resident, after exposure to body fluids, and after removing gloves, significantly increases the risk of infection transmission.
Improper Use of Personal Protective Equipment (PPE)
Incorrect use or failure to use PPE when necessary can lead to the spread of infections. This includes not changing gloves or aprons between tasks or residents and not wearing masks when required.
Waste Management
Improper disposal of healthcare waste (e.g., dressings, disposable clothing) can spread infection. Not segregating waste correctly or failing to dispose of it in a timely manner can lead to environmental contamination.
Lack of Resident Isolation
Not isolating residents with infectious diseases or symptoms promptly can result in widespread outbreaks within the facility. Cohorting symptomatic residents, when single-room isolation is not possible, is essential but also poses a risk if not managed properly.
Poor Ventilation
Inadequate ventilation in care homes can facilitate the airborne spread of pathogens, particularly in areas where residents and staff spend significant amounts of time together.
Shared Facilities and Equipment
The use of communal bathrooms, dining areas, and recreational facilities can contribute to the spread of infections. Similarly, if not properly cleaned between uses, shared equipment can be a transmission source.
Food Hygiene
Improper food handling and preparation can lead to outbreaks of foodborne illnesses. This includes not following proper cooking temperatures, cross-contamination, and inadequate storage of food items.
Water Systems
Legionella and other waterborne pathogens can proliferate in poorly maintained water systems, leading to infections among residents and staff.

What are Infection Prevention and Control (IPC) Principles?
Infection prevention and control in care homes is the set of practices that stop infections entering, spreading within, or leaving a care setting. It covers hand hygiene, personal protective equipment, environmental cleaning, equipment decontamination, waste and linen management, and isolation when someone is infectious.
In a care home, it differs from a hospital in one practical way: residents live there, so IPC has to work inside somebody’s home rather than a clinical environment.
Standard Infection Control Precautions (SICPs): 10 Principles of Infection Control
Standard infection control precautions (SICPs) are the basic IPC measures that reduce the risk of spreading pathogens. NHS England requires all staff to apply them at all times, for all residents, in all care settings, whether an infection is known to be present or not.
When implementing SICPs in care homes and other healthcare settings, it’s crucial to follow a comprehensive approach.
Here are the 10 principles of infection control:

- Patient Placement and Assessment of Infection Risk: Assess every new or returning resident for infection risk before deciding where they are cared for. Place anyone with suspected or confirmed infection in a single room where possible, and reassess as their condition changes.
- Hand Hygiene: Wash with soap and water for at least 20 seconds when hands are visibly soiled or after using the bathroom; use alcohol hand rub at all other moments. Hand rubs should contain emollients to prevent dermatitis, which is itself an infection risk.
- Respiratory and Cough Hygiene: Cover coughs and sneezes with a disposable tissue, dispose of it immediately, and clean hands afterwards. Offer a surgical mask to anyone with respiratory symptoms where it is safe and tolerated.
- Personal Protective Equipment (PPE): Select PPE by the task and the risk of exposure, not by routine. Change gloves and aprons between residents and between tasks on the same resident, and store PPE where it stays clean and is available at the point of use.
- Safe Management of the Care Environment: Clean and disinfect high-touch surfaces and communal areas on a defined schedule, with sign-off. Cleaning and disinfection are separate steps using different products, and doing one does not substitute for the other.
- Safe Management of Care Equipment: Decontaminate reusable equipment after every use and between residents, following the manufacturer’s instructions. Single-use items are never reused, and equipment must be stored clean and dry.
- Safe Management of Healthcare Linen: Bag used linen at the point of generation, never on the floor or carried loose through the home. Segregate infectious linen into the correct colour-coded bag and wash at the specified temperature.
- Safe Management of Blood and Body Fluids: Clean up spillages immediately using the correct product and PPE, and treat all blood and body fluids as potentially infectious regardless of known status. Have a spill kit available where incidents are likely.
- Safe Disposal of Waste (including Sharps): Dispose of waste and sharps into correctly labelled containers in line with local policy. Assemble, date, and sign sharps bins on opening; never fill above the line, and never resheath a needle.
- Occupational Safety and Managing Prevention of Exposure: Have a written procedure for sharps injuries and body fluid exposure that staff can follow without looking it up, including who to report to and the timeframe for post-exposure prophylaxis. Keep staff vaccination records current.
Transmission-Based Precautions (TBPs)
Transmission-Based Precautions (TBPs) are essential strategies in preventing and controlling the spread of infections. TBPs complement SICPs and are implemented when caring for patients with known or suspected infections to manage the routes of transmission specific to infectious agents. TBPs are categorized into Contact, Droplet, and Airborne precautions, each targeting different modes of transmission and requiring specific actions and protective measures.
Contact Precautions are used to prevent infections that spread through direct contact with the patient or indirectly from the patient’s immediate care environment. This includes using personal protective equipment (PPE) like gloves and aprons, and ensuring environmental cleanliness.
Droplet Precautions aim to prevent infections transmitted over short distances through droplets from the respiratory tract. Measures include wearing surgical masks and eye protection when within two meters of the patient, emphasizing the importance of patient placement, and assessing infection risks to manage space effectively in healthcare settings.
Airborne Precautions are necessary for diseases spread via aerosol transmission. This involves using higher levels of respiratory protection (e.g., FFP3 masks), ensuring adequate ventilation, and using isolation rooms with negative pressure where possible. Staff should assess the need for these precautions based on the infectious agent, the severity of the illness, and the setting in which care is provided.
What Does CQC Require for Infection Control in Care Homes?
IPC is assessed as part of CQC’s ongoing assessment of your service, not as a standalone inspection. The COVID-era IPC inspection programme, which rated eight specific areas as “assured”, “somewhat assured” or “not assured”, has been retired.
Under the Single Assessment Framework, infection prevention and control sits within the Safe key question. Inspectors look for evidence that IPC is managed continuously: that audits happen on a schedule, that findings lead to action, that staff training is current, and that the environment reflects the policies on file.
Where the guidance comes from. Three sources matter for a care home in England. The Health and Social Care Act 2008 Code of Practice on the prevention and control of infections is the regulatory baseline CQC assesses against. UKHSA publishes the operational guidance for adult social care, including Understanding and managing infection in adult social care (August 2026) and setting-specific guidance on acute respiratory infection and multidrug-resistant organisms. NHS England’s NIPCM sets out the SICPs themselves. Your own IPC policy should name which versions it follows and when it was last reviewed, because that is what an inspector asks for first.
What this means in practice. CQC gathers evidence between visits as well as during them, so the audit trail from the months before an assessment carries as much weight as what an inspector sees on the day. With CQC targeting 9,000 assessments by September 2026, and services whose ratings predate the framework change facing a materially higher likelihood of assessment, the gap since your last visit is not protection.
The framework itself is changing again: four sector-specific frameworks are expected towards the end of 2026, replacing the 34 quality statements with Key Lines of Enquiry. The five key questions survive, so IPC will continue to be assessed under Safe either way.
👉 Also Read:
→ CQC Quality Statements: A Complete Guide for Care Providers
→ How Health & Social Care Services Can Ensure CQC Compliance
→ A Care Provider’s Guide to CQC Registration Requirements
→ How to Prepare for CQC Inspections with Mock CQC Inspections
→ A Complete Guide to CQC Single Assessment Framework
→ CQC Inspection Checklists & Templates: Prepare for a CQC Visit
How Do You Improve Infection Control in a Care Home?
Here are seven best practices particularly crucial in the unique environment of care homes:
1. Using Personal Protective Equipment (PPE) Correctly
Care home staff must be trained in the correct selection, use, and disposal of PPE, ensuring they understand when and how to use gloves, masks, gowns, and other protective gear. This also involves ensuring PPE is readily available and used appropriately based on the risk of exposure.
Use these free PPE checklists:
2. Infection Control During Resident Admissions
Assessing and managing infection risks during new resident admissions includes performing thorough risk assessments to identify potential infection sources and implementing isolation protocols if necessary.
3. Environmental Cleaning and Disinfection
Maintaining a clean and disinfected environment reduces the risk of infection spread. Routine and targeted cleaning should be prioritized, especially for high-touch areas and resident rooms. Care homes should use disinfectants appropriate to the pathogen and surface, following the manufacturer’s contact time. This practice extends to the prompt cleaning of blood or other potentially infectious material spills.
4. Managing Outbreaks: Isolation and Cohorting Strategies
When outbreaks occur, quickly isolating symptomatic residents and employing cohorting strategies can help prevent further spread. This involves designated areas for infected individuals and careful management of staff and resources to avoid cross-contamination.
5. Engaging Residents and Visitors in Infection Prevention
Educating residents and their families about infection prevention practices helps create a community of care that supports IPC efforts. This includes teaching about hand hygiene, respiratory etiquette, and promptly reporting symptoms or concerns.
6. Regular Training and Education for Care Home Staff
Ongoing training and development for staff on IPC measures are essential. This should cover job-specific practices, emerging infection risks, and updates on guidelines and procedures.
7. Conduct frequent internal audits
Internal infection prevention and control audits are a helpful training tool that helps with all 6 strategies listed above. While it sounds like an additional administrative burden on your teams, using digital tools, you can make internal IPC audits part of day-to-day operations.

Keeping digital records of your regular internal checks also helps demonstrate due diligence and compliance when the time comes for CQC inspections.
Enhance Infection Control in Care Homes with GoAudits
While infection control is rightly considered a priority, embedding ICP measures into the day-to-day care home operations is often a challenge.
Using technology such as the GoAudits care home auditing software can prove effective and beneficial to streamline and enhance IPC protocols in care homes:
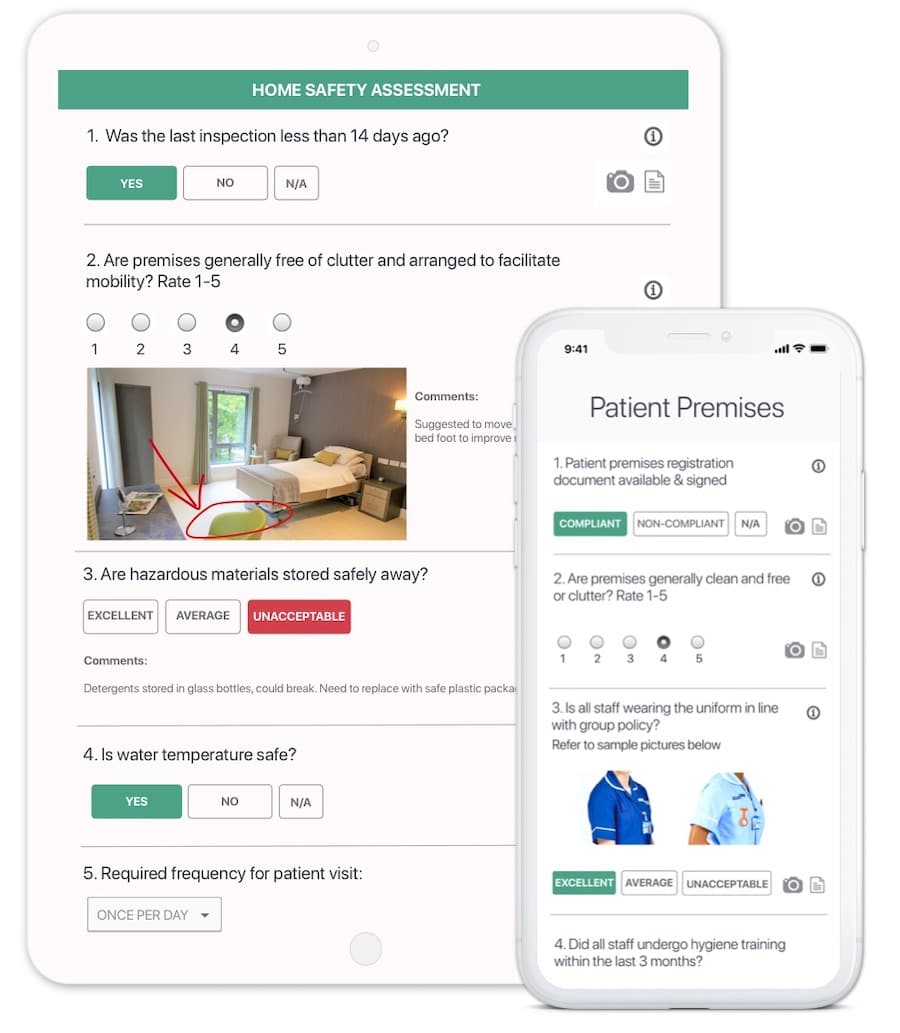
- Enable easy self-inspections with a user-friendly mobile app. Instant reports eliminate paperwork and manual administrative work.
- Start with IPC best practices and other care home audit templates. Easily update digital checklists in case of changes to IPC or local guidelines.
- Standardise IPC procedures and train staff. Create digital checklists for infection control compliance, hand hygiene, cleaning, and more, which all staff members can access on their mobile devices. Schedule regular checks to ensure IPC awareness and compliance.
- Assign corrective actions if issues are found during an IPC audit.
- Keep all digital records and inspection reports in one place. Easily demonstrate compliance during your next CQC inspection and ensure higher CQC ratings.
- The automatic scoring system gives you immediate insights into infection control compliance levels and areas requiring immediate attention.
Beyond infection control, you can also use GoAudits to streamline all internal care home audits.
Continue Reading: How GoAudits helped Careville comply with changing IPC requirements
What Does a Care Home IPC Audit Cover?
A full infection control audit works through six areas. Most care homes audit all six monthly and spot-check the first two weekly.
- Hand hygiene. Observed compliance at the five moments, not self-reported. Sink accessibility, soap and towel availability, alcohol gel at point of care, bare below the elbows.
- Environmental cleanliness. High-touch surfaces, communal areas, resident rooms, and whether the cleaning schedule has actually been signed off. Colour-coded equipment used correctly and stored clean and dry.
- PPE. Availability at point of use, correct selection for the task, donning and doffing technique, and disposal.
- Care equipment. Clean and decontaminate between residents; do not reuse single-use items; store equipment clean.
- Waste, linen and sharps. Segregation, container fill levels, sharps bins assembled, dated and signed, soiled linen handled and bagged at the point of generation.
- Records and governance. Policies current and version-controlled, staff training up to date, outbreak records complete, previous audit actions closed.
The pattern inspectors look for is not a perfect audit. It is a consistent one, with findings that lead to action and actions that get closed.
Care Home Infection Control Audit Templates
GoAudits offers a comprehensive library of healthcare audit checklists designed to improve infection control compliance and quality of care across various healthcare settings, including care homes. These customizable infection prevention audit tools & templates cover a broad range of areas, from general care home audits to specific infection control measures.
- Infection Control Inspection Checklist
- Deep Cleaning for Infection Control
- Hand Hygiene Audit
- Infection Control Audit Template
- Care Home Audit Template
- Care Home Cleaning Checklist – Daily
- Daily Care Home Audit
- Care Home General Observation
- Care Home Audit Checklist
- MAR EMAR Audit Checklist

FAQs
Most homes run a full IPC audit monthly, with weekly spot checks on hand hygiene and environmental cleanliness in between, and an immediate audit after any outbreak. There is no single mandated frequency; what matters is that the interval is defined, documented, and actually kept to. An audit schedule that exists on paper but shows three-month gaps is worse than a less ambitious one that is followed. For the full picture across all care home audits, see our guide to how often to run care home audits.
Area by area rather than task by task, so nothing falls between rooms. For each area: the tasks, the frequency (daily, weekly, monthly, deep clean), who is responsible by name or role, the products and dilution to use, and a sign-off with date and initials. Two things are commonly missed: colour-coded equipment allocation by area, and the clear distinction between cleaning and disinfection, which are different steps with different products. In an outbreak, the schedule should specify enhanced frequency for touch points and isolation areas, so staff are not improvising at the point they are busiest.
Every care home should have a named IPC lead. In most homes this is the registered manager or a senior nurse, and in larger groups there may be a dedicated IPC lead supported by champions on each unit. What matters more than the job title is the authority: the IPC lead needs to be able to stop a practice, order supplies, and escalate to the provider without going through three layers. The role covers maintaining policies, running the audit schedule, leading outbreak response, overseeing training, and liaising with the local health protection team. Name them in the IPC policy, and make sure staff on every shift know who it is.

